Maria stood in the skincare aisle holding two nearly identical-looking boxes, one labeled “0.5% retinol serum” and the other a prescription bag from her dermatologist marked “tretinoin cream, 0.025%.” Her sister had recommended the drugstore version after seeing results in a few weeks.
Her dermatologist had recommended the prescription version after a consultation about fine lines around her eyes. Both were technically part of the same ingredient family, yet the two products behaved so differently on her skin that she wondered if she’d been sold two versions of the same idea, or two entirely different treatments wearing the same marketing language.
That confusion is common, and it comes from the fact that “retinol” and “retinoid” are not interchangeable terms even though shoppers, and sometimes brands, use them as if they were. Retinoid is the umbrella category for every vitamin A derivative used in skincare, from the mildest over-the-counter ester to the strongest prescription compound, which falls under it.
Retinol is just one specific member of that family, a mid-strength option sold without a prescription. Knowing where a product sits on that spectrum changes how quickly it works, how much irritation to expect, and how it should fit into a routine.
Reading the Label: What “Retinol” Means on the Bottle
When a bottle says “retinol,” it means the active ingredient is retinol itself, not one of its weaker cousins or a repackaged prescription compound. Retinol has to convert twice inside the skin before it becomes retinoic acid, the form that binds to skin cell receptors and drives cell turnover. That two-step conversion is part of why retinol is gentler than prescription options a portion of it is lost at each conversion stage, so less active retinoic acid ever reaches the target receptors.
Marketing language complicates this further, since brands often print a percentage on the front of the bottle without clarifying which retinoid form that percentage refers to. A 1% retinol serum and a 1% retinaldehyde serum are not equivalent in strength, and two brands can use identical percentages while delivering different real-world results depending on the base formula, stabilizers, and delivery system layered around the active ingredient. Reading the full ingredient list, not just the front-label percentage, gives a more reliable sense of what a product will do on skin once applied consistently over several weeks.
Products marketed under the retinoid umbrella but sold over the counter usually contain one of these:
- Retinol: the most common over-the-counter form, moderate strength, requires two conversion steps.
- Retinaldehyde (retinal): one conversion step away from retinoic acid, generally faster-acting and slightly more potent than retinol at comparable concentrations.
- Retinyl esters (retinyl palmitate, retinyl acetate): the mildest forms, requiring three conversion steps, often found in “sensitive skin” formulas.
- Encapsulated retinol: retinol wrapped in a delivery system designed to release slowly, reducing surface irritation while extending activity overnight.
None of these require a prescription in most markets, and their strength is loosely tied to how many conversion steps stand between the bottle and active retinoic acid.
Prescription Retinoids and Their Strength
Prescription retinoids skip the conversion process because they already exist as, or convert directly to, retinoic acid. That is the core reason dermatologists reach for them when a patient wants faster or more pronounced results for fine lines, texture, or acne. The tradeoff is a steeper irritation curve during the first several weeks of use, often described as a “retinization” period involving flaking, redness, or sensitivity before the skin adjusts.
A dermatology visit typically starts patients on a lower percentage and shorter frequency, then increases both as tolerance builds. This gradual approach exists precisely because prescription-strength retinoids act faster and harder than anything sold without one, and rushing the process tends to backfire with a compromised skin barrier rather than better results.
Follow-up visits matter more with prescription retinoids than shoppers often expect, since a dermatologist can adjust strength or frequency based on how the skin is responding rather than leaving a patient to guess on their own. Many prescribing physicians schedule a check-in around the six- to eight-week mark, close to when the initial irritation period typically settles and early benefits start becoming visible. That checkpoint also gives patients a chance to flag any unexpected reactions before committing months of a regimen that isn’t working for their particular skin type.
Tretinoin, Adapalene, and Tazarotene: A Closer Look
Three names dominate prescription retinoid conversations, and they are not interchangeable despite frequently being grouped together.
- Tretinoin: the original prescription retinoid, available in creams and gels, widely studied for both acne and photoaging, often considered the benchmark against which newer formulas are measured.
- Adapalene: originally prescription-only but now available over the counter in some regions at 0.1% strength (sold under names like Differin), generally better tolerated than tretinoin while still effective for acne and mild textural concerns.
- Tazarotene: often regarded as the strongest of the three, approved for both acne and psoriasis in some formulations, and typically reserved for patients who have already built tolerance to other retinoids.
Adapalene’s move to over-the-counter shelves blurred the line between retinol and retinoid categories further, since it behaves like a prescription-strength ingredient without requiring a prescription anymore. Shoppers now have to check the active ingredient name rather than assuming “over the counter” automatically means “gentle.”
Pricing patterns add another layer of confusion to this landscape. Generic tretinoin, when covered by insurance or purchased through a pharmacy without brand markup, can cost less per month than a premium over-the-counter retinol serum, even though it delivers a stronger effect on skin. Brand-name prescription options and dermatologist-exclusive skincare lines sometimes carry a price premium disconnected from raw ingredient strength, which means cost alone is a poor signal of where a product sits on the retinoid spectrum. Comparing the active ingredient and its listed concentration remains the more reliable way to judge value across competing products.
Building Tolerance Without Wrecking Your Skin Barrier
Whichever form someone chooses, the skin needs an adjustment period. Jumping straight to nightly use of a stronger retinoid is one of the most common reasons people give up on the ingredient category entirely within the first month.
A more sustainable approach looks like this:
- Start at low frequency: two or three nights a week for the first two to three weeks, regardless of product strength.
- Buffer with moisturizer: applying a plain moisturizer before or after the retinoid product can blunt irritation without eliminating benefits.
- Watch for barrier signs: stinging, persistent redness, or flaking that doesn’t calm within a day or two suggests the frequency needs to drop, not push through.
- Increase slowly: add one additional night per week only after the skin has stopped reacting noticeably to the current frequency.
- Avoid stacking actives: combining a new retinoid with strong exfoliating acids in the same routine often overwhelms the barrier before either ingredient gets a fair trial.
Dermatologists frequently point out that consistency at a lower, tolerable frequency beats an aggressive schedule that gets abandoned after two irritated weeks.
A technique sometimes called “moisturizer sandwiching” applying a layer of moisturizer, then the retinoid, then another light layer of moisturizer on top gives beginners an extra buffer during the adjustment period without diluting the product enough to eliminate its benefits entirely.
Some dermatologists also recommend applying retinoids every third night rather than a fixed weekly count, which spreads exposure more evenly for people whose skin reacts unpredictably from one week to the next. Whichever method gets used, the goal stays the same: give the skin barrier enough recovery time between applications that irritation doesn’t compound night after night.
Pairing Ingredients: What Works and What Fights Back
Retinoids interact with other active ingredients in ways that matter for a routine’s overall effectiveness. Some pairings support the retinoid’s job; others cancel it out or amplify irritation past a useful point.
Ingredients that tend to pair well include:
- Ceramide-based moisturizers: help rebuild the lipid barrier that retinoids can temporarily thin.
- Hyaluronic acid: adds hydration without adding exfoliation, making it a low-risk layering partner.
- Niacinamide: often used alongside retinoids to calm redness and support barrier repair.
Ingredients that usually need separation, either by using them on alternating nights or at different times of day, include benzoyl peroxide (which can oxidize and deactivate some retinoid formulas), strong AHA or BHA exfoliants (which compound dryness and peeling), and vitamin C in unstable formulations (better used in the morning while retinoids are reserved for night).
Sunscreen deserves a mention here too, even though it isn’t an active ingredient in the traditional sense. Because retinoid use increases photosensitivity, pairing a nighttime retinoid routine with a consistent, broad-spectrum sunscreen the following morning functions almost like a companion step rather than a separate skincare category entirely. Skipping sunscreen on the days after retinoid use is one of the more common reasons people experience worsening pigmentation or sun damage despite otherwise diligent skincare habits, since the skin sits more vulnerable to UV exposure precisely when protection matters most.
Morning Routine Versus Night Routine Considerations
Retinoids are almost universally recommended for nighttime use, partly because some forms degrade in sunlight and partly because the skin’s repair processes are more active overnight. That scheduling choice shapes the rest of a routine.
Morning routines built around a retinoid regimen tend to prioritize sun protection above nearly everything else, since retinoid-treated skin is more sensitive to UV exposure and sunburn risk rises during the adjustment period. A broad-spectrum sunscreen becomes non-negotiable rather than optional.
Evening routines, meanwhile, typically follow a cleanse-dry-treat sequence, with many dermatologists recommending the skin be completely dry before retinoid application to reduce the chance of irritation from enhanced penetration on damp skin.
The order of steps within an evening routine also affects how a retinoid performs on the skin. Applying it directly after cleansing, before heavier moisturizers or facial oils, generally allows for more consistent penetration, while layering it beneath thick occlusive creams can dilute its effect a fair amount.
Some people prefer applying retinoid products roughly twenty minutes after cleansing to let the skin settle and reduce the odds of stinging, a small adjustment that costs nothing but can noticeably change how a sensitive complexion tolerates the ingredient over the following weeks of use.
Pregnancy, Sensitivity, and Other Reasons to Pause
Retinoids, both over-the-counter and prescription, are generally advised against during pregnancy and breastfeeding. This guidance applies broadly across the vitamin A derivative family, including retinol, because of concerns tied to vitamin A metabolites and fetal development, even though topical absorption is much lower than oral vitamin A intake. Anyone who is pregnant, trying to conceive, or breastfeeding should raise retinoid use directly with an obstetrician or dermatologist rather than making the call independently.
Beyond pregnancy, several other situations call for caution or a pause:
- Active eczema or rosacea flares: retinoids can intensify inflammation during an active flare.
- Recent procedures: chemical peels, laser treatments, or waxing near the treated area usually require a retinoid break before and after.
- Sunburned or windburned skin: applying a retinoid to already-compromised skin barrier tends to worsen sensitivity.
- New medication interactions: certain oral acne medications and other prescriptions can compound retinoid sensitivity, worth flagging to a prescribing doctor.
For anyone pregnant or breastfeeding who still wants an active ingredient targeting texture or fine lines, alternatives like azelaic acid or certain vitamin C formulations are generally considered safer choices, though adding anything new to a routine during pregnancy is worth confirming with an obstetrician first rather than assuming a product is safe simply because it isn’t labeled a retinoid. Many people resume their usual retinoid routine after breastfeeding ends, picking up roughly where they left off at a similarly tolerated frequency and strength.
Choosing a Product for Your Skin Type
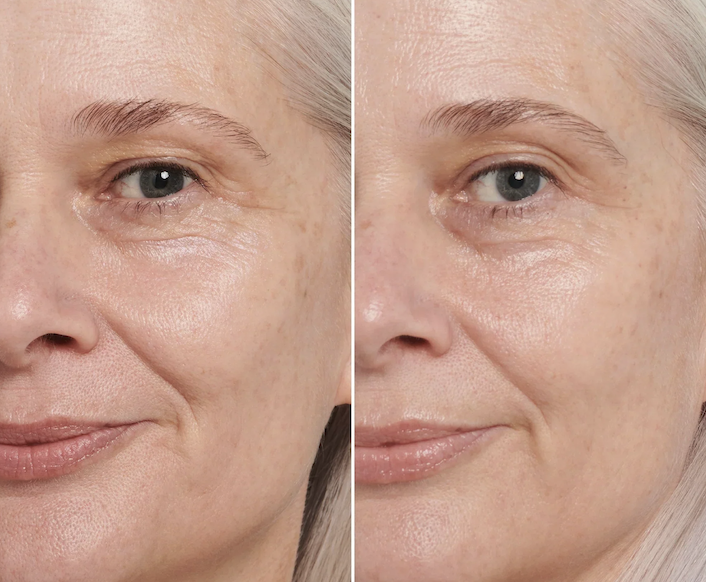
Skin type and personal goals should guide which end of the retinoid spectrum makes sense to start with. Someone with naturally oily, resilient skin dealing with early fine lines might tolerate a mid-strength retinol without much trouble. Someone with reactive, easily flushed skin might do better starting with an encapsulated or ester-based formula and working up slowly, if at all, toward stronger options.
Dry or mature skin often benefits from cream-based retinoid formulations rather than gels, since gels tend to be more drying. Acne-prone skin, on the other hand, often responds well to gel textures and to adapalene specifically, given its long track record with breakouts alongside texture concerns. None of these guidelines replace a conversation with a dermatologist, especially for anyone with a diagnosed skin condition, since a professional can weigh in on formulation, frequency, and whether prescription strength is worth pursuing at all.
Patch testing any new retinoid product on a small area, such as the inner forearm or a discreet patch of jawline, for a few nights before applying it across the whole face is a simple habit that catches sensitivity issues early. It won’t predict every reaction, since facial skin often behaves differently than skin elsewhere on the body, but it does flag obvious intolerance before a person has committed a full bottle and several weeks to a product that was never going to agree with their skin in the first place.
Final Thoughts
Retinol and retinoids sit on the same spectrum, not in separate categories, and the differences between them come down to strength, conversion steps, and how quickly the skin reacts. A drugstore retinol serum and a prescription tretinoin cream can both deliver real improvements in texture and fine lines, but they demand different levels of patience and caution.
The best starting point usually isn’t the strongest option available it’s whichever formulation a person can use consistently without damaging their skin barrier along the way. Anyone dealing with persistent acne, diagnosed skin conditions, pregnancy, or uncertainty about which strength fits their skin should loop in a dermatologist before building a long-term routine around any vitamin A derivative.
Frequently Asked Questions
1. Is retinol the same as Retin-A?
No. Retin-A is a brand name for tretinoin, a prescription retinoid that converts directly to active retinoic acid. Retinol is a separate, weaker compound that requires two conversion steps in the skin before it becomes active, which is why it’s sold over the counter while Retin-A is not.
2. How long does it take to see results from retinol?
Most people notice initial texture changes within six to eight weeks of consistent use, with more visible improvements in fine lines and tone appearing closer to the three- to six-month mark. Prescription retinoids can show changes somewhat faster, though the adjustment period often takes longer to get through first.
3. Can I use retinol and vitamin C together?
They can coexist in the same routine, but many dermatologists suggest using vitamin C in the morning and retinoids at night to reduce the chance of irritation and to keep each ingredient working under the conditions it performs best in.
4. Does retinol make skin more sensitive to the sun?
Yes, retinoids of all strengths can increase sun sensitivity, especially during the first few weeks of use. Daily broad-spectrum sunscreen is generally recommended for anyone using a retinoid product, regardless of season.
5. What’s the difference between retinol and bakuchiol?
Bakuchiol is a plant-derived ingredient marketed as a retinol alternative, and some research suggests it can offer comparable benefits for texture and fine lines with less irritation. It doesn’t belong to the retinoid family chemically, though, so its mechanism and long-term evidence base differ from traditional retinoids.
6. Should I switch from retinol to a prescription retinoid?
That depends on personal goals, skin tolerance, and how much progress the current product has delivered. A dermatologist consultation is the most reliable way to decide, since they can assess skin condition directly and recommend a strength and formulation suited to individual needs rather than general assumptions.








